A low-lying cerebellar tonsil on an MRI does not automatically mean that you have a dangerous brain abnormality or need surgery. By understanding the anatomy, symptom patterns, associated spinal-cord changes, imaging process, and treatment trade-offs, you can have a more productive discussion about what the finding means in your case.
Key takeaways
- Chiari I involves downward displacement of the cerebellar tonsils through the foramen magnum.
- MRI findings matter most when they match symptoms or obstruct cerebrospinal fluid flow.
- Syringomyelia is a fluid-filled cavity within the spinal cord that can change treatment decisions.
- Observation fits some symptom-free cases; decompression enters discussion with significant symptoms or complications.
What Arnold Chiari Malformation Is—and Which Type You Have
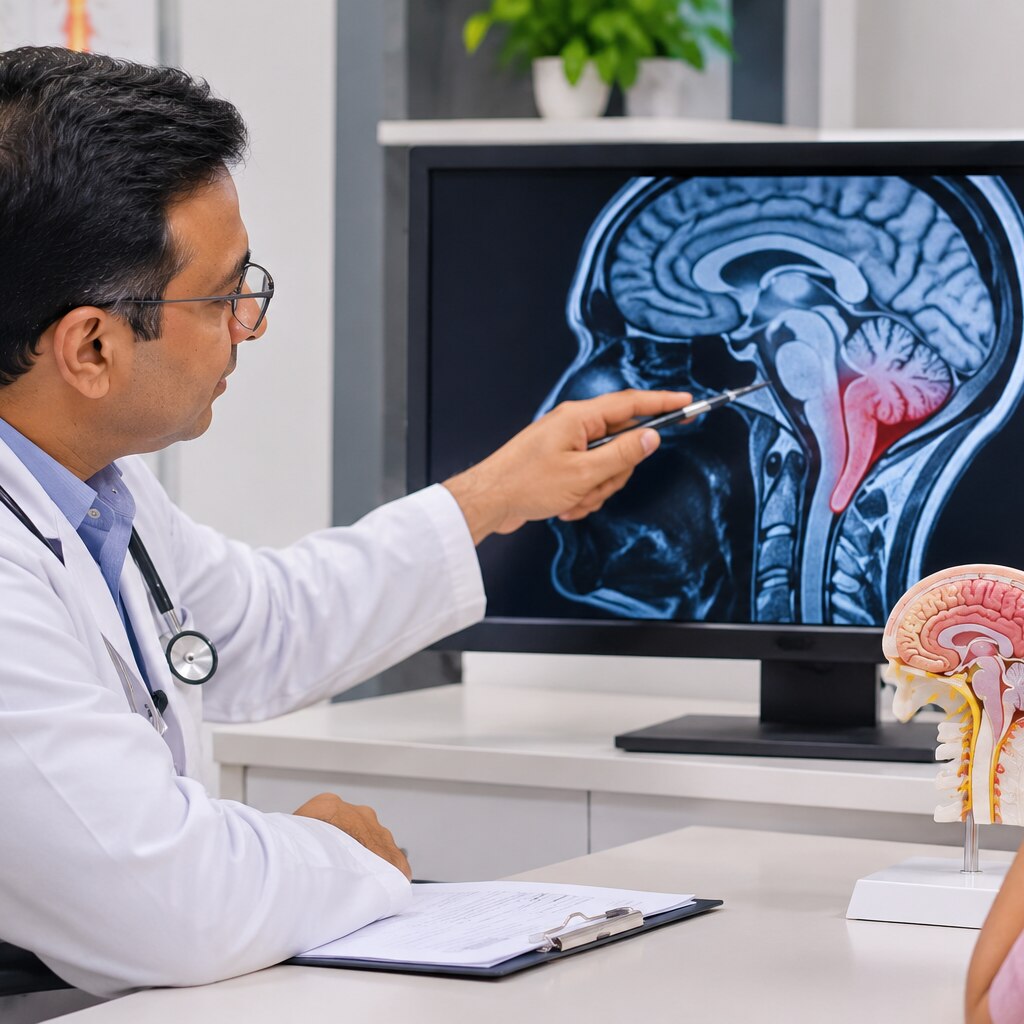
Chiari malformation describes abnormal positioning of structures at the base of the skull, where the brain meets the spinal cord. In Chiari I, the cerebellar tonsils extend downward through the foramen magnum, the opening in the skull’s base, and may crowd the brainstem, upper cervical spinal cord, or the normal flow of cerebrospinal fluid (CSF).
The cerebellum helps coordinate movement and balance; the brainstem carries vital nerve pathways between the brain and spinal cord.
Arnold-Chiari malformation is an older umbrella term. The main types differ substantially:
| Type | Typical anatomy | Usual context |
|---|---|---|
| Chiari I | Downward displacement of the cerebellar tonsils | Often found incidentally in children or adults |
| Chiari II | More extensive hindbrain displacement and structural abnormalities | Usually associated with myelomeningocele and hydrocephalus |
| Chiari III | Severe malformation with hindbrain tissue extending into an occipital or upper-neck encephalocele | Rare and serious |
| Chiari IV | Marked underdevelopment or absence of cerebellar tissue | Extremely rare; classification is less consistent |
A low-lying tonsil on MRI does not prove clinically important Chiari I. A descent near 5 mm is a commonly used radiologic reference, but crowding, tonsil shape, neural compression, and blocked CSF flow matter too. Some people have no symptoms and need observation rather than surgery.
Tonsillar descent can also be acquired from intracranial hypotension, hydrocephalus, intracranial hypertension, a mass lesion, or spinal traction. These causes must be considered before labelling the finding a congenital Chiari malformation.
How Chiari Can Affect the Brainstem, Cerebellum, and Spinal Cord
The strongest symptom clue is an occipital headache worsened by coughing or straining, sneezing, laughing, or lifting. It reflects pressure changes at the crowded foramen magnum and often lasts seconds to minutes, unlike an ordinary tension headache.
| Structure | Symptoms that raise concern | What they may indicate |
|---|---|---|
| Brainstem | Trouble swallowing, choking, a changed or hoarse voice, involuntary eye movements, double vision, reduced gag reflex, or sleep-disordered breathing | Pressure on pathways controlling swallowing, eye movement, voice, and breathing |
| Cerebellum | Unsteady walking, poor coordination, clumsiness, or difficulty judging movement | Disrupted balance and movement control |
| Upper cervical spinal cord | Numbness, tingling, burning pain, weakness in an arm or leg, stiffness, or reduced ability to feel pain and temperature | Irritation or compression of the cord and its sensory or motor pathways |
These symptoms do not prove that Chiari is responsible. Dizziness, headache, imbalance, and numbness have many other causes, so the pattern on examination and MRI matters more than a single symptom or the number of millimetres of tonsil descent.
Seek prompt medical assessment for worsening weakness, repeated choking, fainting, breathing pauses during sleep, or loss of bladder control. In a child, new scoliosis can be an important sign of a Chiari-related spinal-cord problem, particularly when an associated syrinx is present.
Syringomyelia and Other Findings That Change the Picture
A syrinx is a fluid-filled cavity within the spinal cord. Chiari-related blockage at the foramen magnum can disrupt cerebrospinal-fluid flow and allow this cavity to form or enlarge. It may damage cord pathways that carry pain and temperature signals, causing reduced sensation, hand weakness or wasting, stiffness, or pain.
A whole-spine MRI matters because a limited brain scan can miss a clinically important finding. Imaging may show:
- Syringomyelia, including the cavity’s level and size
- Hydrocephalus, meaning excess cerebrospinal fluid in the brain’s ventricles
- Scoliosis, or a sideways spinal curvature
- Tethered cord, where spinal-cord traction restricts movement
- A mass lesion that crowds the brainstem or alters cerebrospinal-fluid flow
In a child, scoliosis may be the first visible sign of a syrinx or another spinal-cord problem. Chiari plus scoliosis therefore calls for assessment of the entire spinal cord, not a decision based only on a head MRI.
Low-lying tonsils do not automatically prove congenital Chiari I. Before assigning that diagnosis, clinicians look for acquired causes such as:
- Intracranial hypotension from low cerebrospinal-fluid pressure
- Intracranial hypertension from raised pressure
- Hydrocephalus
- A brain or spinal mass
- Spinal traction
A progressive neurological deficit, an enlarging or symptomatic syrinx, or clear cerebrospinal-fluid obstruction changes the treatment discussion. Bladder or bowel dysfunction signals more advanced cord involvement and needs prompt medical assessment.
How Doctors Confirm Whether Low-Lying Tonsils Are Clinically Important
A 5-mm measurement is a clue, not a diagnosis. Doctors interpret tonsillar descent alongside the shape of the tonsils, crowding at the foramen magnum, compression of the brainstem or upper spinal cord, and symptoms that fit those findings.
| Pattern | Findings that support it | What doctors check |
|---|---|---|
| Symptomatic congenital Chiari I | Headache triggered by coughing or straining, imbalance, sensory change, weakness, or other objective neurological findings | MRI of the brain and entire spinal cord for crowding, syringomyelia, hydrocephalus, spinal curvature, or tethered cord |
| Incidental descent | No matching neurological deficit and only nonspecific complaints such as ordinary headache, fatigue, or dizziness | Whether the tonsils are crowded and whether another diagnosis better explains the symptoms |
| Acquired descent | A new change in tonsil position caused by intracranial hypotension, intracranial hypertension, a mass lesion, hydrocephalus, or spinal traction | Brain imaging, contrast when indicated, and examination for the underlying disorder |
The examination tests eye movements, balance, coordination, reflexes, strength, sensation, swallowing, and gait. A child’s scoliosis can be the first important clue to a syrinx, so head imaging alone is inadequate when spinal curvature is present.
A cine MRI measures cerebrospinal-fluid movement at the foramen magnum. Obstructed flow strengthens the case that crowding is clinically relevant, but it does not replace the history, neurological examination, and search for acquired causes.
When Observation Is Reasonable and When Decompression Enters the Discussion
An incidental Chiari I finding without symptoms or syringomyelia usually calls for clinical review and MRI follow-up, not preventive surgery. A tonsil measurement near 5 mm does not decide the issue; symptoms, crowding, neural compression, and CSF-flow obstruction matter more.
1. Continue observation when neurological examination is stable, symptoms are absent or mild and non-progressive, and imaging shows no syrinx or significant CSF blockage. Follow-up should track headaches, swallowing, balance, limb strength, sensation, and repeat MRI findings.
2. Discuss surgery when neurological impairment progresses, a syrinx causes symptoms or enlarges, or imaging and examination show clear CSF-flow obstruction that fits the clinical picture. Cine MRI can show disturbed CSF movement when the decision is uncertain, but it cannot determine surgical need by itself.
3. Before choosing posterior fossa decompression or foramen-magnum decompression, confirm that tonsillar descent is not caused by intracranial hypotension, hydrocephalus, a mass lesion, intracranial hypertension, or spinal traction. Ask which structures will be removed or opened, whether dural grafting is planned, and what benefit is realistic.
The trade-off includes CSF leak and pseudomeningocele, infection or meningitis, wound problems, bleeding, craniocervical instability, neurological deterioration, and persistent or recurrent symptoms. Dr Amit Aiwale-Best Neurosurgeon in Thane can help review the MRI, examination, CSF-flow evidence, and proposed technique before you weigh those risks.
Frequently asked questions
What is Arnold Chiari malformation?
Chiari malformation is abnormal positioning of structures at the skull base. In Chiari I, the cerebellar tonsils extend through the foramen magnum and may affect the brainstem, spinal cord, or cerebrospinal fluid flow.
How can Chiari malformation affect the brain and spinal cord?
Crowding can affect the brainstem, cerebellum, upper cervical spinal cord, and cerebrospinal fluid circulation. Effects depend on the malformation’s type and associated findings.
What is syringomyelia, and why does it matter?
Syringomyelia is a fluid-filled cavity within the spinal cord. Its presence can indicate disrupted cerebrospinal fluid flow and influence evaluation and treatment planning.
How do doctors determine whether low-lying cerebellar tonsils are clinically important?
Doctors compare symptoms with MRI findings, assess crowding and cerebrospinal fluid flow, and look for spinal cord changes such as syringomyelia.
When is Chiari malformation observed instead of treated with surgery?
Observation can be reasonable when symptoms are absent or mild and imaging shows no concerning complication. Decompression enters discussion when symptoms, cerebrospinal fluid obstruction, or spinal cord changes are significant.